01Reserve Geometry and the Reserve-Setting Cycle
Cirsentra is a computational physiology lab building a physiological model of patient health: how a patient’s state arises, sustains disease, and changes with treatment and recovery. It is the foundation for patient-state medicine: treatment chosen from the state the patient is in and the part of the response that is failing.
Between a biomarker and a diagnosis lies the physiology that decides the response: what reaches the tissue, whether its receptors work, whether its cells can do the work, and whether they recover. We name the operation that is failing, and test it by changing it.
Each discovery explains one part of how the body receives a demand, responds to it and recovers afterwards: how capacity is built, what reaches a tissue, whether its receptors work, whether its cells can afford the work, how organs coordinate, and what a response leaves behind. Together they are the parts of our physiological model of patient health.
We built them from original computational analyses of human biological data, including maps of the receptors and cellular machinery different cells carry, and from published experimental and clinical research. Each card opens a page with what we found, what it means for patients, and the experiment that tests it. Further down, the discoveries are put in order, step by step.
01Reserve Geometry and the Reserve-Setting Cycle
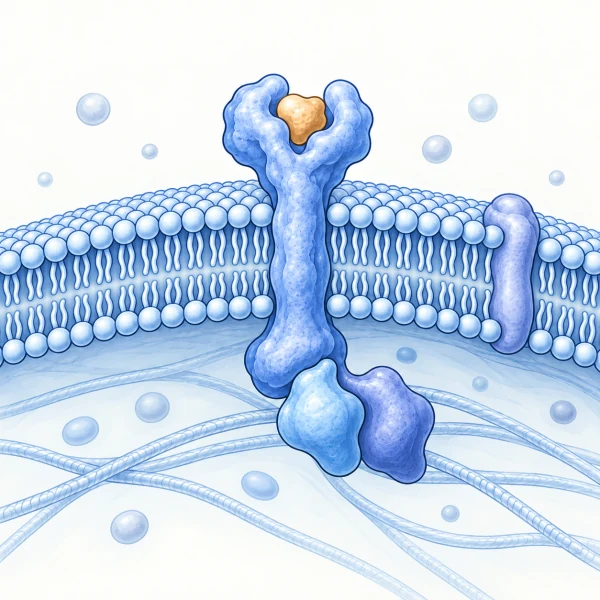
02The Competent Receiver
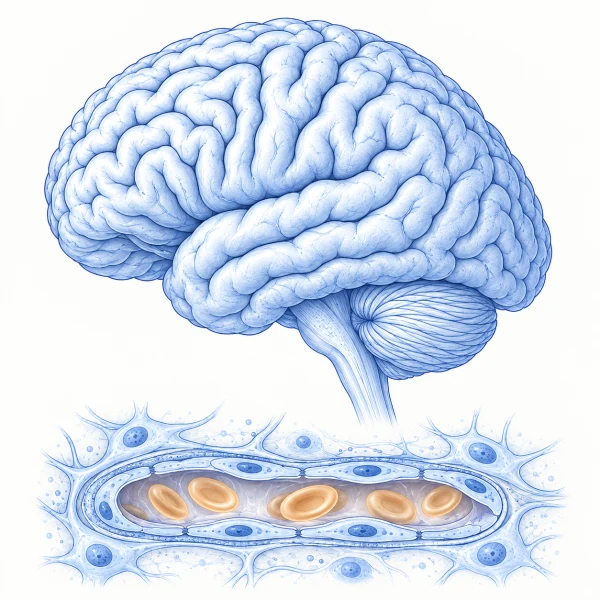
03The Circumventricular Sentinel Network
04Systemic Metabolic Readability
05Sex- and life-stage receiver architecture
06The First Reserve
07External Effectors
08Energy Resistance
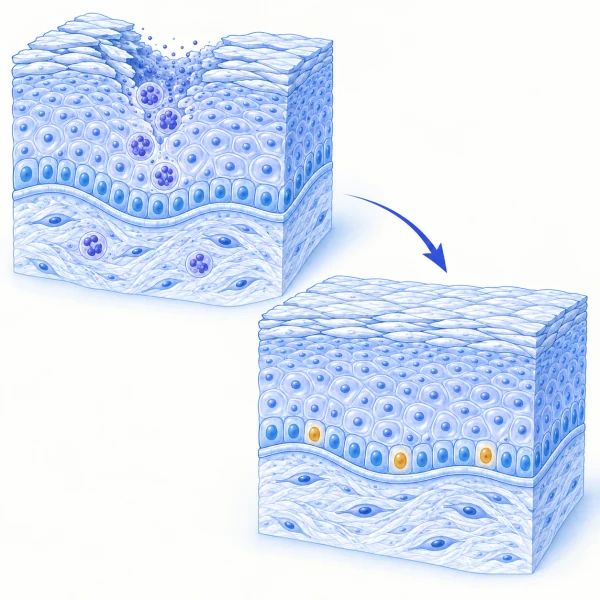
09Biological State Memory
10The Convergence Cell
A blood test shows how much of a hormone is in the blood, not what the body does with it. Between the blood and the brain sit the cells lining blood vessels, and they meet every hormone and inflammatory signal first.
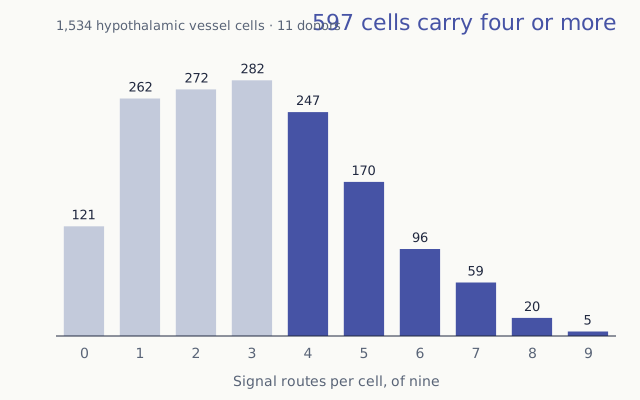
We examined 1,534 of these cells from the human hypothalamus, the brain region that steers hormones, appetite and body temperature. Many single cells carry the RNA for receptors of four or more different body signals at once, shown in dark blue. A separate group of 20,120 vessel cells from 30 people showed the same pattern.
This suggests that one signal can change how the next one gets through, so the same blood level could act differently in different people. Our next experiments test that directly.
Explore discoveryEach bar counts vessel cells by how many of nine body signals they carry receptor RNA for. Dark bars: four or more.
How the discoveries connect
The discovery cards above each answer one question. Here they are put in order: the eight steps that every demand on the body passes through, whether it is a treatment, a meal, an infection or an injury. A treatment can fail at any one of these steps, and each failure needs a different fix.
Under each step we describe what failure looks like in a patient, and link the discovery that explains it.
Before and after birth, the body builds the organs, blood vessels and receptors that every later demand will draw on.
In a patientA person starts adult life with less to work with, and the same illness costs them more.
What a body can do today depends on how it was built, its condition now, and what it has been through: past illness, treatment, age and sex.
In a patientTwo people with the same diagnosis are in different states, so the same treatment meets two different bodies.
A hormone, a drug, a microbe or an injury releases active substances. What counts is the form that actually reaches the tissue, and by which route.
In a patientThe blood level looks right, but the tissue receives too little, too much, or something harmful.
Gateways in the brain, and the cells lining blood vessels, sample what the blood carries and set how the rest of the body answers.
In a patientA signal is misread at the gateway, and the brain sends the wrong command to the rest of the body.
A hormone or a drug only works if a working receptor is there to catch it and pass the message on.
In a patientThe drug reaches its target, but the target is damaged or missing, so little happens.
Carrying out the response costs energy and materials. Cells must do today’s work and still rebuild their receptors for tomorrow.
In a patientThe instruction arrives and is received, but the cell cannot afford to carry it out.
After a meal or a dose, several organs must each do their part at the right time, and what one organ does changes what the others receive.
In a patientOne organ holds a result steady by overworking, and the strain shows up somewhere else.
Afterwards the body clears up, rebuilds what it used, and keeps some changes.
In a patientA person looks recovered, but less capacity has returned, and the next illness or dose meets a weaker body.
Then the cycle repeats. The next demand, whether an infection, a meal or the next dose, meets the body this response left behind, back at step 02. That is why we measure a response twice, with one standard: challenge, recover, rechallenge.
The method
We measure a response, what it cost and how the body recovered, then ask for the same function again.
Read the methodThe papers
Eleven foundational preprints each set out one part of the science behind our discoveries: the state of the body, how each response changes it, and how to measure that change in people. Two more apply them to aging and cancer. An integrating paper joins all of them into one physiological model of patient health.
Building a Physiological Model of Patient Health
The General Causal-State Theorem Between Cause and Phenotype
Physiological Adaptation, Recovery, and Aging
The State-Update Law Between One Biological Challenge and the Next
The Dynamic Target-Capacity Law in Physiology, Pharmacology, and Recovery
Insulin resistance as a failure of cross-organ coordination
The Challenge-Recovery-Rechallenge Standard for Mechanistic Physiology
A graded endothelial architecture and the Convergence Gate model of hypothalamic control
A coupled rate law for compensatory cost and task-specific failure at the neuroendocrine interface
How sources, delivery routes and receiver recovery shape disease
A Distributed Causal Architecture from Source State to Organ Failure
How host conditions, usable machinery and reconstruction determine later function
How systemic inputs, receiver competence, and recovery shape malignant and host function
Our hallmarks research
We connect the hallmarks of aging and cancer to what they do to a patient’s capacity: the function a person keeps with age, and what both the tumour and the patient can still do during treatment.
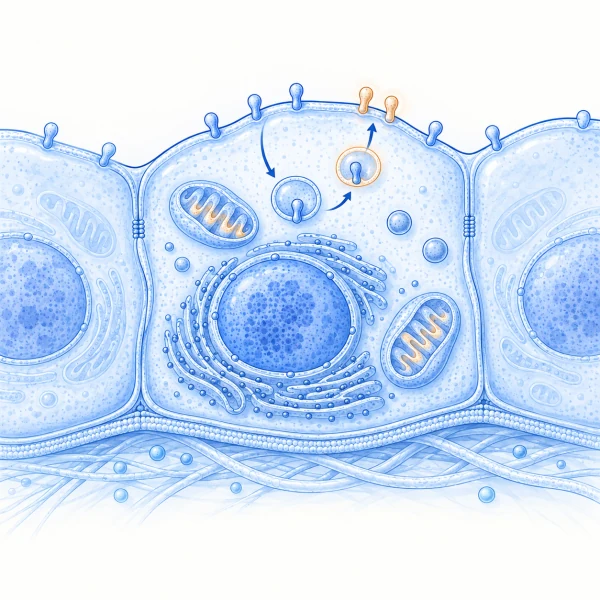
Hallmarks of Aging
A person’s routine results can stay stable while recovering from illness, exercise or surgery becomes harder. We connect aging to the gradual loss of the body’s ability to repair and rebuild, and ask which present conditions can still be changed.
Explore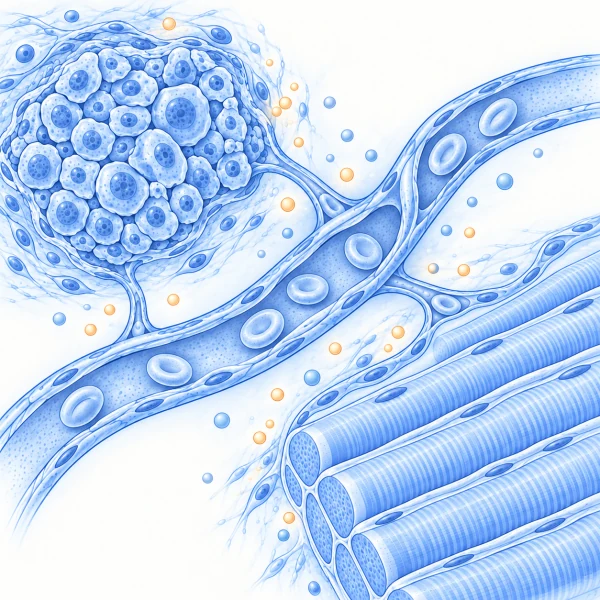
Hallmarks of Cancer
The same early tumour response can leave two patients in different states. We follow the tumour and the host together, so treatment can control the cancer and preserve the patient’s function.
ExploreWhat we are working on
For each condition below we are building a complete mechanistic physiological model of patient state: how the disease arises and keeps going, which step limits the patient at each stage, and what has to change for function to return.
Which step of the response is failing, in which patients, and at which stage of the disease.
Tests that locate the failing step, so the treatment can be matched to it.
Including targets that protect or rebuild the capacity a treatment needs.
Why one heart or brain recovers after an acute event and another does not.
What keeps nerve cells working, and what stops them rebuilding.
How signals from the body shape mood, appetite and seizure control.
What is built before and after birth, and what an inherited defect changes.
Why several body systems stop recovering together.
Why muscle is lost, and what it needs to rebuild.
Oncology applications
Cancer treatment can control the tumour while the patient’s own function declines. These applications follow both at once, and find the host failure that can still be corrected.
Pancreatic ductal adenocarcinoma (PDAC)
During treatment with a RAS inhibitor such as daraxonrasib, tumour control and the patient’s function can move on different paths. We find the failure that threatens the patient next, such as blocked digestion, pancreatic insufficiency, appetite loss, treatment-related injury, infection or failed tissue renewal, and match the correction to it. Routine care data come first; a mechanistic assay is added only when it changes the decision.
Colorectal cancer (CRC)
The same approach for colorectal cancer: follow tumour control and the patient’s function together, name the limitation that appears during treatment, match the correction, and prove that it restores function without weakening tumour control.
A new host treatment advances only if it restores useful, repeatable function while tumour control stays intact.
Applications
Our foundational science guides new ways to identify who may benefit from a treatment, assess whether a drug target can work, and develop therapies and clinical trials around lasting functional benefit.
Explore applicationsIdentify which patients may benefit, and why.
Find what limits function.
Assess whether a target can deliver the intended response.
Restore the capacity a treatment needs.
Design trials to explain benefit, failure and durability.
Make health information easier to understand and discuss.
We welcome scientific collaborators, clinical partners, pharmaceutical developers and investors working to improve treatment, recovery and healthy longevity.
Contact us to discuss research collaboration, patient stratification, assay development, drug-target assessment, therapeutic programmes or clinical-trial design and support.